


Infertility with Endometriosis and Adenomyosis
Trouble getting pregnant can be the first sign of endometriosis or adenomyosis, even when you otherwise feel fine. Both can affect ovulation, fertilization and implantation, and both can be treated with your family plans in mind.
- How common
- Common
- When to get checked
- No need to wait a full year
- Good to know
- It can be the first sign
Medically reviewed by Dr. Steven Vasilev, MD
Board-Certified Gynecologic Oncologist & Integrative Medicine Diplomate, Advanced Robotic Endometriosis Excision Surgeon, Director of Lotus Endometriosis Institute · Updated Oct 2026
Does this sound like you?
Tap any that fit. We'll turn them into a note you can bring to your visit.
None of these? If you're worried about your fertility, it's still worth a conversation. Speak with us
When to get help
Getting checked early matters, because fertility planning is time-sensitive. With painful periods or pelvic pain, see an endometriosis specialist without waiting a full year of trying.
Keep track
Note how long you've been trying, your cycle length and any ovulation tracking, past pregnancies, your pain and bleeding patterns, and any earlier scans or surgeries. It's the most useful thing to bring to your first visit.
Speak with Us
Book a visit any time you're unsure, and especially if you've been trying for:
- 12 months, if you're under 35
- 6 months, if you're 35 or older
- About 6 months, if endometriosis or adenomyosis is known or suspected
- Less time, if both apply, or after endometriomas, pelvic surgery or a miscarriage
- Less time, with painful periods, pelvic pain, pain with sex or heavy bleeding
Your first visit
We go through your history and your notes, then map out next steps together, whether that's tests, imaging or treatment.
When it needs a specialist: Surgery and IVF for endometriosis
What it can feel like
How patients often describe it
- Every negative test feels like another loss.
- We've been trying for over a year.
- My periods seemed normal enough, so no one looked.
- I'm told everything looks fine, but nothing's happening.
Infertility often doesn't feel like a physical symptom. It can feel like time passing, month after month of hope and disappointment, and it can weigh on sleep, mood and relationships. When endometriosis or adenomyosis is involved, it may come with painful periods, pelvic pain or pain during sex, but not always; some people have few other symptoms at all. Some notice it more with age, after stopping birth control or after a miscarriage.
Why it happens
Endometriosis
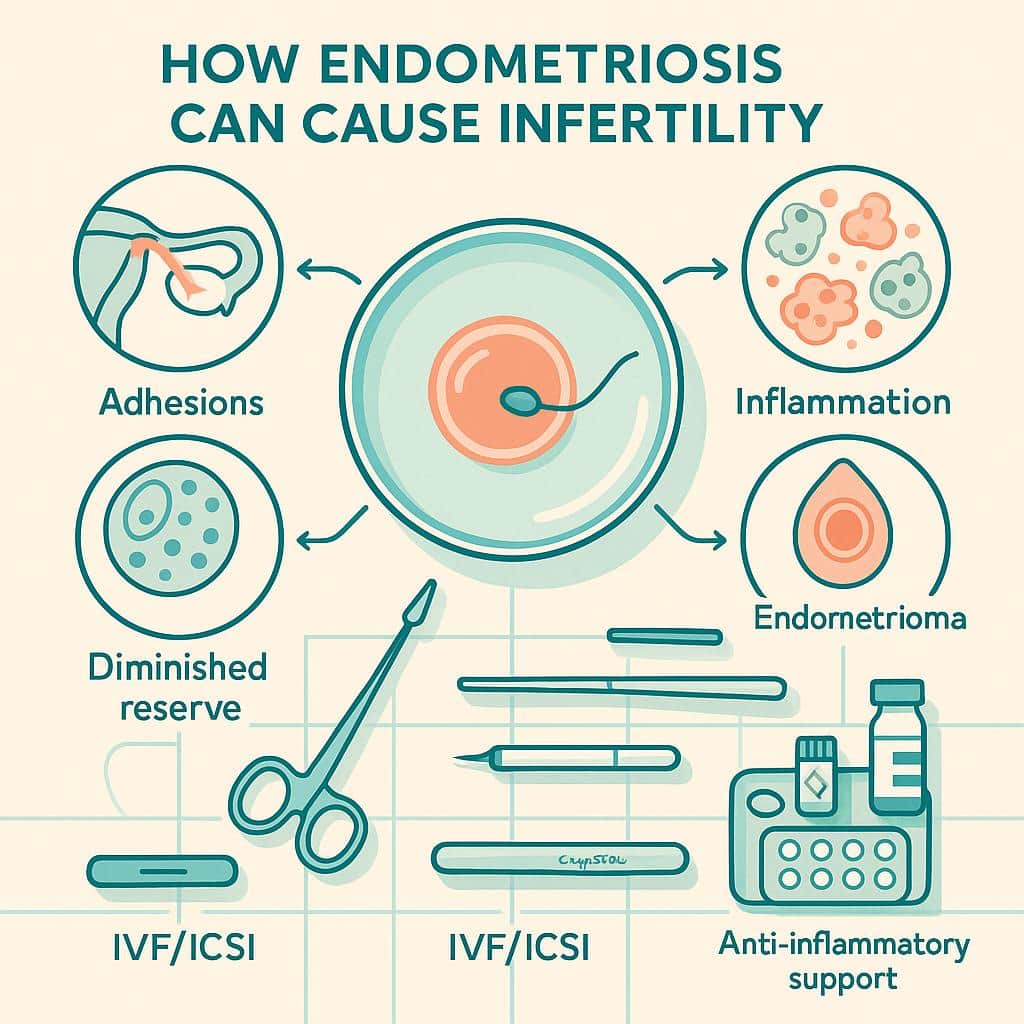
In endometriosis, tissue similar to the uterine lining grows outside the uterus. It inflames the pelvis and can form scar tissue (adhesions) that tethers the ovaries and tubes, so the tube can't easily pick up the egg. Inflammation may also affect egg quality, sperm function and fertilization, and ovarian cysts called endometriomas may lower ovarian reserve, your supply of eggs.
Adenomyosis
In adenomyosis, similar tissue grows into the muscle wall of the uterus. It can change how the uterus contracts and raise inflammation in its lining, which may make implantation harder and raise the risk of early pregnancy loss for some people. The two conditions often occur together.
Other causes often sit alongside, from ovulation problems and thyroid disease to male-factor infertility, which is why both partners are usually evaluated.
“Infertility is sometimes the first time endometriosis gets noticed. If you're not getting clear answers, a specialist can look for disease that routine fertility tests miss, and plan treatment around your timeline.”
Why it's often missed
Endometriosis can be missed on a standard ultrasound, and many people with it have few other symptoms. So a fertility workup can come back normal without anyone looking for it, and when it's there, the usual advice to keep trying for a year can delay answers.
Severity isn't a reliable guide either. Some people with minimal disease struggle to conceive while others with advanced disease don't, so the decision to look further rests on your history as much as on your scans.
How it's diagnosed
Fertility basics
Ovulation tracking, a semen analysis and a check of ovarian reserve, such as an AMH blood test. These cover common causes for both partners.
Expert imaging
An ultrasound or MRI read by someone trained in endometriosis can show endometriomas, deep disease and adenomyosis. A normal scan doesn't rule endometriosis out.
Checking the tubes
A test such as an HSG shows whether your fallopian tubes are open. Blocked or damaged tubes change which treatment makes sense.
Laparoscopy, when needed
If endometriosis is suspected, laparoscopy can confirm it and remove it in the same operation. An endometriosis specialist plans its timing around your fertility goals.
Treatment options
Your plan depends on your age, your timeline and whether you're aiming for natural conception or fertility treatment.
- Surgical
Excision surgery
Removes endometriosis at the root when it distorts the pelvis or causes pain, which can improve the chances of conceiving for some people. Surgery on the ovaries is planned to protect your egg supply.
Surgery overview - Medical
Well-timed hormonal therapy
Can ease pain or bleeding while you plan next steps, and in select cases, such as adenomyosis before IVF, calm the disease first. Most options prevent pregnancy while you take them, so timing matters.
Hormonal Therapy - Fertility
IVF and fertility care
Can be the next step with blocked tubes, lower ovarian reserve or limited time. We coordinate with fertility specialists.
- Support
Pelvic floor therapy
Can help when pain during sex makes trying difficult.
Pelvic Floor Therapy - Support
Supportive care
Sleep, anti-inflammatory meals, stress support and pain care that fits your fertility plans.
Integrative Medicine
Trying to conceive with endometriosis?
We look for the causes routine tests miss and plan treatment around your timeline.
Schedule a ConsultationPrefer to talk it through? Call or text us.
Questions people ask
Does endometriosis always cause infertility?
No, endometriosis does not always cause infertility, and many people with endometriosis conceive without assistance. It can make it harder to get pregnant for some patients, especially when inflammation or scarring affects the ovaries, fallopian tubes, or pelvic anatomy.
Can endometriosis cause infertility without pain?
Yes, endometriosis can present with little or no pain, and infertility may be the first or only sign. It can affect fertility through ongoing inflammation, scar tissue that changes pelvic anatomy, and effects on the ovaries and egg quality.
Can adenomyosis affect fertility or pregnancy?
Yes, adenomyosis can affect fertility and pregnancy, although not everyone will struggle to conceive. It may interfere with implantation and is associated with higher risks of miscarriage and preterm birth, especially with more diffuse disease.
Do endometriomas affect fertility or ovarian reserve?
Yes, endometriomas can affect fertility and may be associated with lower ovarian reserve in some patients. Surgery, especially repeat cyst surgery, can also affect ovarian reserve because healthy ovarian tissue can be removed or its blood supply altered.
Can endometriosis surgery improve my chances of conceiving?
Excision surgery can improve the chances of conceiving for some patients with endometriosis, particularly when removing superficial disease helps restore more normal pelvic anatomy. Outcomes vary, and surgery on the ovaries can affect ovarian reserve.
How long to try conceiving before infertility evaluation?
If you suspect or know you have endometriosis, we generally recommend a fertility evaluation after about 6 months of trying naturally. We suggest evaluation sooner if you’re over 35, have severe symptoms, or have been told you may have ovarian cysts or tubal involvement.
Often happens with
Read more

Sources & medical review
Reviewed by Dr. Steven Vasilev, MD, Board-Certified Gynecologic Oncologist & Integrative Medicine Diplomate, Advanced Robotic Endometriosis Excision Surgeon, Director of Lotus Endometriosis Institute. Last reviewed Oct 2026; next review Oct 2027.
- Carson SA, Kallen AN. Diagnosis and management of infertility: a review. JAMA. 2021;326(1):65–76.
- Bonavina G, Taylor HS. Endometriosis-associated infertility: from pathophysiology to tailored treatment. Front Endocrinol (Lausanne). 2022;13:1020827.
- Vercellini P, Consonni D, Dridi D, et al. Uterine adenomyosis and in vitro fertilization outcome: a systematic review and meta-analysis. Hum Reprod. 2014;29(5):964–977.
- Becker CM, Bokor A, Heikinheimo O, et al. ESHRE guideline: endometriosis. Hum Reprod Open. 2022;2022(2):hoac009.