


Bowel Endometriosis Surgery
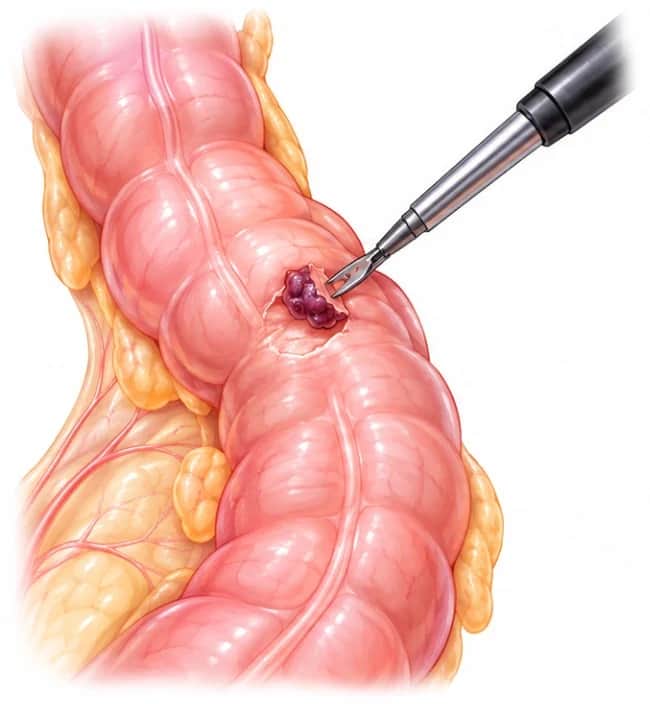
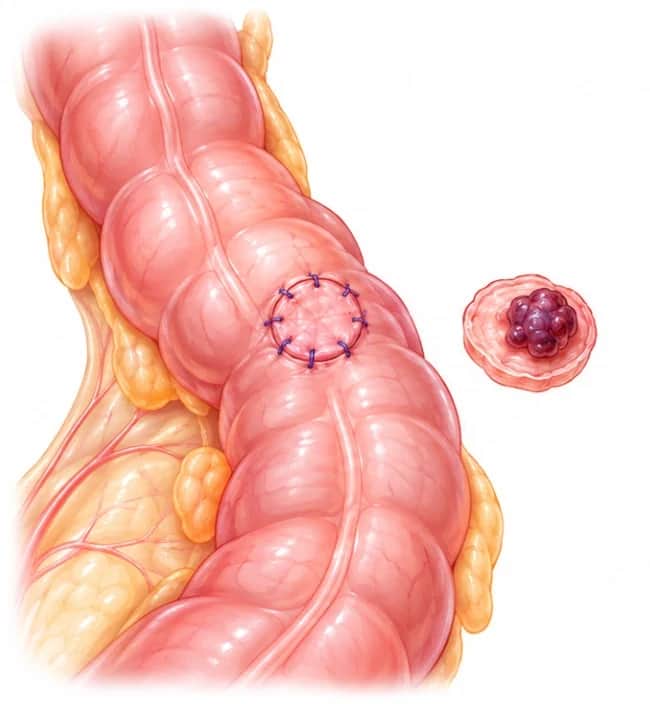
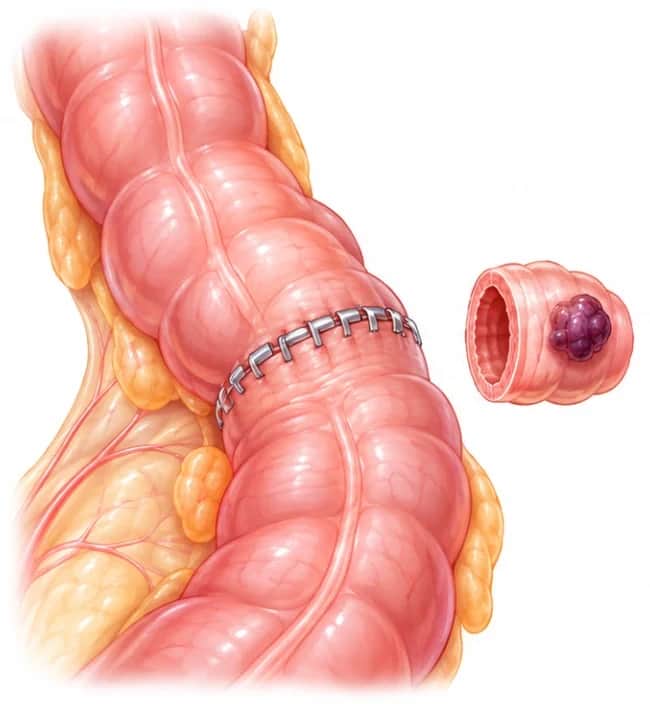
When endometriosis reaches the bowel, usually the rectum or sigmoid colon, surgery removes it while sparing as much bowel as possible: shaved off the surface, a small disc cut out, or, only when it's needed, a short segment removed. All of it planned before the day.
- How
- Robotic, sparing the bowel whenever possible
- Who operates
- Gynecologic oncologist, credentialed in bowel surgery
- Hospital stay
- Depends on what the bowel needs
Medically reviewed by Dr. Steven Vasilev, MD
Quadruple board-certified in surgical and integrative therapies, Minimally-Invasive Robotic Endometriosis-Excision Surgeon, Director of Lotus Endometriosis Institute · Updated Oct 2026
Why the least bowel removed matters
The aim is the smallest step that still removes all the disease. Going further than needed adds risk and a longer recovery; stopping short leaves disease behind. That's why the choice is made for your bowel, from your imaging, and agreed with you in advance.
Is it right for me?
When bowel symptoms flare with your period, imaging shows a nodule on the bowel, or medication eases the pain but the disease stays.
Usually worth considering if
- Bowel symptoms that follow your cyclePain with bowel movements, constipation or diarrhea, or bloating that flares around your period.
- Rectal bleeding with your periodUncommon, but a strong sign when it happens.
- Imaging shows a bowel noduleOn MRI, or an ultrasound done by an endometriosis expert.
- Medication helps, but not enoughHormones can calm the pain; they don't remove a nodule in the bowel wall.
- Signs of narrowingConstipation that keeps getting worse, or a feeling that something is stuck.
- Told it was "just IBS"A normal colonoscopy doesn't rule it out: the disease grows from the outside of the bowel in.
Often improves
- Pain with bowel movements, and bowel symptoms that follow your cycle
- Deep pelvic pain and pain with sex
- A narrowed bowel, opened up again
- Fertility, for some patients, when the pelvis is freed
Won’t fix on its own
- IBS or other bowel conditions that aren't endometriosis
- A lifetime cure: endometriosis is a chronic disease
That's why the bowel is checked properly before surgery, and why care continues after it with pelvic floor therapy and, when it fits, hormonal therapy.
Many bowel symptoms in endometriosis come from disease next to the bowel, not in its wall, and need no bowel surgery at all. Imaging and a consultation tell you which.
How does it compare?
Three techniques, from least to most bowel removed. Which one depends on how deep, how large and how many the nodules are.
| Compared | Shaving | Disc excision | Removing a segment |
|---|---|---|---|
| What's removed | The disease, peeled off the bowel surface | A small, full-thickness disc of bowel wall; the opening is closed | A short piece of bowel; the ends are joined again |
| Used when | The disease sits on the surface or the outer muscle | One deeper nodule, in one spot | Long or several nodules, or the bowel is narrowed |
| The bowel | Stays whole | Stays whole, with a repair | A short piece is gone |
| Recovery | Like excision elsewhere in the pelvis | Longer, while the repair heals | The longest; bowel habits can take a while to settle |
| Main risks | The lowest of the three | A leak from the repair (uncommon) | A leak where the ends join (uncommon); rarely, a temporary stoma |
Shaving
- What's removed
- The disease, peeled off the bowel surface
- Used when
- The disease sits on the surface or the outer muscle
- The bowel
- Stays whole
- Recovery
- Like excision elsewhere in the pelvis
- Main risks
- The lowest of the three
Disc excision
- What's removed
- A small, full-thickness disc of bowel wall; the opening is closed
- Used when
- One deeper nodule, in one spot
- The bowel
- Stays whole, with a repair
- Recovery
- Longer, while the repair heals
- Main risks
- A leak from the repair (uncommon)
Removing a segment
- What's removed
- A short piece of bowel; the ends are joined again
- Used when
- Long or several nodules, or the bowel is narrowed
- The bowel
- A short piece is gone
- Recovery
- The longest; bowel habits can take a while to settle
- Main risks
- A leak where the ends join (uncommon); rarely, a temporary stoma
What happens, step by step?
A video consultation, mapping the bowel with specialized imaging, a plan for each possibility, then one operation.
Before surgery
Planning consultation
By video, with your symptoms, imaging and any earlier operative reports. Dr. Vasilev explains which of the three techniques your bowel may need, and why.
Mapping the bowel
An ultrasound done by an endometriosis expert, or MRI, shows how deep a nodule goes and how many there are. Sometimes a second kind of ultrasound, or a colonoscopy, adds detail.
More about Mapping the bowel
A vaginal and a rectal ultrasound together can show the bowel wall layer by layer. Imaging guides the plan; the final call on the bowel is made during surgery, within what you agreed to beforehand.
Your plan
Which bowel steps might be needed, what each means for your recovery, and your consent to them in advance, so the operation doesn't stop halfway. Insurance and a fixed price are settled before anything is booked.
Surgery day
The operation
Robotic, through small incisions. All the endometriosis in the pelvis is removed, and the bowel gets the least it needs: shaving, a disc, or a segment.
Often in the same operation: endometriosis excision · bladder and ureter surgery
More about The operation
Dr. Vasilev is a gynecologic oncologist, trained and credentialed in bowel surgery. When a case calls for it, a colorectal surgeon joins the team, planned in advance rather than called in on the day.
In the hospital
Most often it is still a same-day outpatient procedure. When it isn't, how long you stay depends on what the bowel needed: shortest after shaving, longer after a disc or a segment, until your bowel is working again.
Recovery
- Weeks 1–3
Early recovery
Walking from the start. Many people are back to light activity and desk work in 2–3 weeks. Food builds from soft and gentle back to normal.
- Around a month
Full activity
Most people return to full activity around a month; longer after a segment, when bowel habits can take time to settle.
Follow-up
- 3 months
Follow-up
Your pathology results and a video check-in, with pelvic floor therapy or a plan to keep it from coming back if you need one.
Who should do it?
A surgeon who can do all three, so the choice follows your bowel, not the limits of the surgeon's training.
Bowel endometriosis is where surgeons differ most. One who can only shave may leave deep disease behind; one who mostly removes segments may take bowel that could have been spared. Dr. Vasilev is a gynecologic oncologist, trained and credentialed in bowel surgery, so he can do all three and choose what your bowel needs.
“Most bowel endometriosis can be removed without removing bowel segments. The skill is knowing when that's possible, and when it isn't.”
Patients often ask
Shaving vs disc vs bowel resection for endometriosis: what’s the difference?
Shaving removes disease from the bowel surface, disc excision removes a full-thickness piece of bowel wall, and segmental resection removes a bowel segment and reconnects the ends. The choice depends on lesion depth, size and location, bowel narrowing, symptoms and your goals.
Will endometriosis excision surgery need bowel resection or a stoma?
Most endometriosis excision surgeries do not require a bowel resection, and a stoma is uncommon. These possibilities come up mainly when endometriosis grows deep into the bowel wall or scar tissue has significantly distorted the anatomy.
How long is recovery after bowel endometriosis surgery?
Most people can resume light daily activities and many types of work in about 2–3 weeks, with full activity often around one month. Recovery after bowel endometriosis surgery can take longer when the procedure is more complex.
Do medications help bowel endometriosis, and when is surgery needed?
Hormonal medications can reduce pain in many patients with bowel endometriosis, but they don’t remove deep bowel nodules. Surgery is more strongly considered for narrowing or obstruction risk, severe pain despite medication, recurrent rectal bleeding with cycles, or fertility-focused treatment.
You’re on step 1 of 3
Next: Who should operate?What to look for in any surgeon, and Dr. Vasilev’s results.