



Hyperbaric Oxygen Therapy for Endometriosis
How HBOT may affect lesions and symptoms, what evidence exists, and where it may fit in care.
Hyperbaric oxygen therapy may have a complementary role
Hyperbaric oxygen therapy for endometriosis is being investigated as a complementary treatment that may help symptoms and healing in select patients. It functions best alongside established care, not as a substitute for excision surgery or medical management. Its biological rationale and early observations are promising, but large randomized human trials remain limited.
What HBOT does and why oxygen may matter
Oxygen delivery in a pressurized chamber
Hyperbaric oxygen therapy (HBOT) involves breathing 100% oxygen in a chamber pressurized above normal atmospheric pressure. This allows more oxygen to dissolve into the bloodstream and reach tissues, significantly increasing tissue oxygen levels.
HBOT has long-standing applications in wound healing, radiation injury, decompression sickness, and chronic infections. Its proposed role in endometriosis centers on changing the low-oxygen environment that helps lesions survive and grow, rather than acting on hormones or pain pathways alone.
Low-oxygen conditions around lesions
Endometriosis lesions frequently exist in low-oxygen conditions, called hypoxia. This environment drives inflammation, new blood vessel formation, scarring, and pain signaling. Hypoxia-inducible factors (HIFs), proteins that help cells respond to low oxygen, are increased within endometriotic tissue and support lesion survival and progression.
A 2016 laboratory study examining endometrial tissue and an ovarian endometriotic cell line found increased HIF-1α and miR-210, a molecule involved in regulating cell activity, in ectopic lesions. In cells grown under low-oxygen conditions, miR-210 helped preserve cell survival and promoted autophagy, a process through which cells recycle their components.
These findings help explain how endometriotic cells adapt to low oxygen. The 2016 laboratory study did not test HBOT, however, so it supports the biological rationale rather than demonstrating a treatment benefit. By raising tissue oxygen levels, HBOT may counteract these hypoxia-driven pathways.
Potential effects on lesions and symptoms
Inflammation, blood vessels, and lesion activity
HBOT may reduce inflammation both around lesions and throughout the body. It may also reduce HIF signaling and inhibit angiogenesis, the formation of new blood vessels that support lesions.
In animal models, exposure to hyperbaric oxygen has been shown to decrease the size and activity of endometriotic implants and lower levels of inflammatory cytokines, the chemical messengers involved in inflammation. These are animal findings, not established outcomes for people receiving HBOT for endometriosis.
Could HBOT Fit Your Endometriosis Care?
Our specialists are here to help you understand your condition and explore your treatment options.
Schedule a ConsultationCellular repair and immune responses
Other potential effects include improved mitochondrial function, cellular repair, and immune regulation. Mitochondria supply energy for cells, so improving their function may help address tissue dysfunction and support healing.
Together, these proposed effects make tissue oxygen levels a distinct treatment target. Whether they translate into lasting symptom relief in people still needs clarification.
What the evidence shows so far
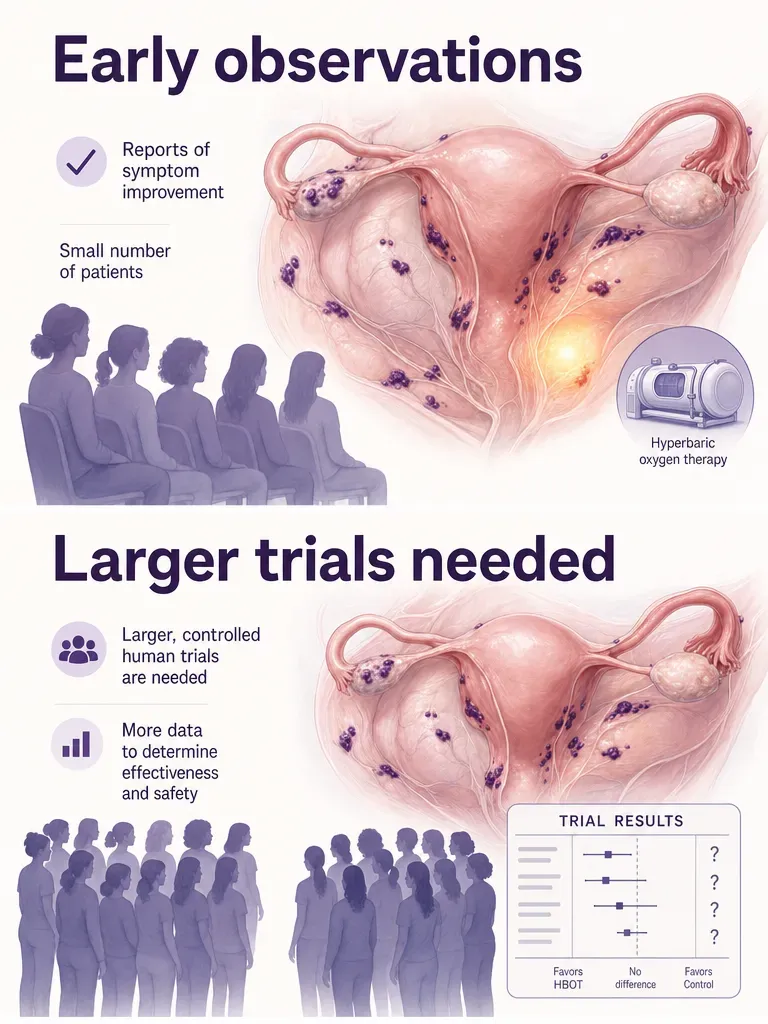
Early clinical observations and limited studies suggest that HBOT may alleviate pelvic pain and improve endometriosis symptoms. Some reports also describe reduced blood vessel supply within lesions and lower inflammatory markers following treatment.
Large-scale randomized controlled trials in humans remain limited, and HBOT is not regarded as a standalone therapy. Further clinical work is needed to establish treatment protocols, identify who is most likely to benefit, and clarify long-term outcomes.
Where HBOT may fit in a treatment plan
Situations in which it may be considered
HBOT may be considered for select patients within an integrative treatment plan, particularly when persistent inflammation, impaired healing, or complex pain syndromes are present. Its role is complementary: it does not replace excision surgery or medical management.
Discuss with your own doctor what specific benefit HBOT is intended to provide and how it would fit alongside other treatment. If you’d like a specialist’s second opinion on a proposed treatment plan, our team can review your options.
Sessions and treatment setting
Protocols vary, but treatment typically involves multiple sessions over several weeks. HBOT should be administered in an accredited medical facility under physician supervision.
Before committing to a course of treatment, useful questions for your doctor include:
- What symptom or healing problem would HBOT target in my case?
- How would it fit alongside my current medical treatment or a recommendation for excision surgery?
- What session schedule and treatment duration are you recommending, and why?
- How would we assess whether it is helping?
Safety and screening before HBOT
Careful screening is needed before starting HBOT. Potential risks include ear or sinus barotrauma, meaning injury caused by pressure changes, and temporary vision changes.
Oxygen toxicity is a concern with prolonged exposure. Claustrophobia can also make the chamber difficult to tolerate and should be part of the pretreatment discussion.
Ask the clinician supervising HBOT:
- Could my medical history or existing ear, sinus, or vision problems affect treatment?
- How does the proposed protocol limit the risk of oxygen toxicity?
- How would difficulty tolerating the chamber be handled?
- What screening will be completed before my first session?
References
Becker CM, et al. Hypoxia and endometriosis. Hum Reprod Update. 2011;17(6):771–783. DOI: 10.1007/s43032-025-02024-0
Wu MH, et al. Hypoxia promotes the survival of endometriotic cells. Am J Pathol. 2007;170(1):272–284. PMID: 26914112
Erdem M, et al. Effects of hyperbaric oxygen therapy on endometriosis in an experimental rat model. Fertil Steril. 2013;99(3):864–870.
Thom SR. Hyperbaric oxygen therapy. J Intensive Care Med. 2011;26(3):131–145. DOI: 10.1371/journal.pone.0339455
Quick Answers
When is hysterectomy recommended for adenomyosis?
Hysterectomy is typically considered for adenomyosis when severe symptoms come from the uterus and you’re not planning future pregnancy. It is usually weighed most strongly when conservative treatments haven’t provided acceptable relief, aren’t tolerated, or don’t fit your goals.
Why does ovarian cyst pain keep coming back?
Ovarian cyst pain can return because new cysts form with ovulation, a cyst persists or comes back, or nearby endometriosis or scar-like bands cause pain. An endometrioma, a cyst caused by endometriosis, may be associated with deeper pelvic disease.
Why do I have chronic fatigue and pelvic pain?
Chronic fatigue and pelvic pain can come from endometriosis, adenomyosis, or more than one condition. Inflammation, disrupted sleep, heavy bleeding and ongoing pain can drive fatigue, while the nervous system can become more pain-sensitive over time.
Why is my period pain so severe that it disrupts my daily life?
Severe period pain that disrupts daily life may signal endometriosis, adenomyosis, or another underlying cause. Worsening pain, poor relief with NSAIDs and heat, heavy bleeding, or pain between periods warrant evaluation, even when imaging looks normal.